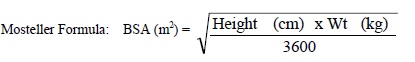
NEVIRAPINE TABS 200 MG 60CT
Generic: Nevirapine
NEVIRAPINE TABS 200 MG 60CT
Sign up to see pricing
Licensed pharmacies, clinics, doctor's offices, and veterinary practices get instant account approval
Sign Up — Instant ApprovalDrug Information
Identification
Nevirapine
Nevirapine
Camber Pharmaceuticals, Inc.
HUMAN PRESCRIPTION DRUG
Administration
TABLET
ORAL
ANDA078584
Active Ingredients
| Ingredient | Strength |
|---|---|
| NEVIRAPINE | 200 mg/1 |
Pharmacological Class
Data sourced from openFDA / DailyMed. For full prescribing information, consult the drug label.
Wholesale compliance resources
Drug Resources
Clinical Drug Information
Indications & Usage
1 INDICATIONS AND USAGE Nevirapine tablets are indicated in combination with other antiretroviral agents for the treatment of human immunodeficiency virus (HIV-1) infection in adults and pediatric patients 15 days and older [see Clinical Studies (14.1 , 14.2) ] . Limitations of Use: Based on serious and life-threatening hepatotoxicity observed in controlled and uncontrolled trials, nevirapine tablets are not recommended to be initiated, unless the benefit outweighs the risk, in: adult females with CD4 + cell counts greater than 250 cells/mm 3 or adult males with CD4 + cell counts greater than 400 cells/mm3 [see Warnings and Precautions (5.1) ] . Nevirapine tablet is an NNRTI indicated in combination with other antiretroviral agents for the treatment of human immunodeficiency virus (HIV-1) infection in adults and pediatric patients 15 days and older. ( 1 ) Limitations of Use: Based on serious and life-threatening hepatotoxicity observed in controlled and uncontrolled trials, nevirapine tablet is not recommended to be initiated, unless the benefit outweighs the risk, in: adult females with CD4 + cell counts greater than 250 cells/mm 3 adult males with CD4 + cell counts greater than 400 cells/mm 3 ( 1 , 5.1 )
Dosage & Administration
2 DOSAGE AND ADMINISTRATION The 14-day lead-in period must be strictly followed; it has been demonstrated to reduce the frequency of rash. ( 2.4 , 5.2 ) If any patient experiences rash during the 14-day lead-in period, do not increase dose until the rash has resolved. Do not continue the lead-in dosing regimen beyond 28 days. ( 2.4 ) If dosing is interrupted for greater than 7 days, restart 14-day lead-in dosing. ( 2.4 ) Adults (≥16 yrs) Pediatric Patients* (≥15 days) First 14 days 200 mg once daily 150 mg/m 2 once daily After 14 days 200 mg twice daily 150 mg/m 2 twice daily *Total daily dose should not exceed 400 mg for any patient. 2.1 Adult Patients The recommended dose for nevirapine is one 200 mg tablet daily for the first 14 days, followed by one 200 mg tablet twice daily, in combination with other antiretroviral agents. The 14-day lead-in period with nevirapine tablets 200 mg daily dosing must be strictly followed as the lead-in period has been observed to decrease the incidence of rash [see Dosage and Administration (2.4) and Warnings and Precautions (5.2) ] . If rash persists beyond the 14-day lead-in period, do not dose escalate to 200 mg twice daily. The 200 mg once-daily dosing regimen should not be continued beyond 28 days, at which point, an alternative regimen should be sought. For concomitantly administered antiretroviral therapy, the manufacturer’s recommended dosage and monitoring should be followed. 2.2 Pediatric Patients The recommended oral dose for pediatric patients 15 days and older is 150 mg/m 2 once daily for 14 days followed by 150 mg/m 2 twice daily thereafter. The total daily dose should not exceed 400 mg for any patient. formula.jpg 2.3 Monitoring of Patients Intensive clinical and laboratory monitoring, including liver enzyme tests, is essential at baseline and during the first 18 weeks of treatment with nevirapine tablets. The optimal frequency of monitoring during this period has not been established. Some experts recommend clinical and laboratory monitoring more often than once per month, and in particular, would include monitoring of liver enzyme tests at baseline, prior to dose escalation, and at two weeks post-dose escalation. After the initial 18-week period, frequent clinical and laboratory monitoring should continue throughout nevirapine tablets treatment [see Warnings and Precautions (5) ] . In some cases, hepatic injury has progressed despite discontinuation of treatment. 2.4 Dosage Adjustment Patients with Rash Discontinue nevirapine tablets if a patient experiences severe rash or any rash accompanied by constitutional findings [see Warnings and Precautions (5.2) ] . Do not increase nevirapine tablets dose if a patient experiences mild to moderate rash without constitutional symptoms during the 14-day lead-in period of 200 mg/day (150 mg/m 2 /day in pediatric patients) until the rash has resolved [see Warnings and Precautions (5.2) ] . The total duration of the once daily lead-in dosing period should not exceed 28 days at which point an alternative regimen should be sought. Patients with Hepatic Events If a clinical (symptomatic) hepatic event occurs, permanently discontinue nevirapine tablets. Do not restart nevirapine tablets after recovery [see Warnings and Precautions (5.1) ] . Patients with Dose Interruption For patients who interrupt nevirapine tablets dosing for more than 7 days, restart the recommended dosing, using one 200 mg tablet daily (150 mg/m 2 /day in pediatric patients) for the first 14 days (lead-in) followed by one 200 mg tablet twice daily (150 mg/m 2 twice daily for pediatric patients). Patients with Renal Impairment Patients with CrCl greater than or equal to 20 mL per min do not require an adjustment in nevirapine tablets dosing. The pharmacokinetics of nevirapine have not been evaluated in patients with CrCl less than 20 mL per min. An additional 200 mg dose of nevirapine tablets following each dialysis treatment is indicated in patients requiring dialysis. Nevirapine metabolites may accumulate in patients receiving dialysis; however, the clinical significance of this accumulation is not known [see Clinical Pharmacology (12.3) ] .
Adverse Reactions
6 ADVERSE REACTIONS The most common adverse reaction is rash. In adults, the incidence of rash is 15% versus 6% with placebo, with Grade 3/4 rash occurring in 2% of subjects. ( 6.1 ) In pediatric subjects the incidence of rash (all causality) was 21%. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Hetero Labs Limited at 1-866-495-1995 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. 6.1 Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Clinical Trial Experience in Adult Patients The most serious adverse reactions associated with nevirapine are hepatitis, hepatic failure, Stevens-Johnson syndrome, toxic epidermal necrolysis, and hypersensitivity reactions. Hepatitis/hepatic failure may be isolated or associated with signs of hypersensitivity which may include severe rash or rash accompanied by fever, general malaise, fatigue, muscle or joint aches, blisters, oral lesions, conjunctivitis, facial edema, eosinophilia, granulocytopenia, lymphadenopathy, or renal dysfunction [see Boxed Warning and Warnings and Precautions (5.1 , 5.2) ] . Hepatic Reaction In controlled clinical trials, symptomatic hepatic events regardless of severity occurred in 4% (range 0% to 11%) of subjects who received nevirapine and 1% of subjects in control groups. Female gender and higher CD4 + cell counts (greater than 250 cells/mm 3 in women and greater than 400 cells/mm 3 in men) place patients at increased risk of these events [see Boxed Warning and Warnings and Precautions (5.1) ]. Asymptomatic transaminase elevations (AST or ALT greater than 5X ULN) were observed in 6% (range 0% to 9%) of subjects who received nevirapine and 6% of subjects in control groups. Co-infection with hepatitis B or C and/or increased transaminase elevations at the start of therapy with nevirapine are associated with a greater risk of later symptomatic events (6 weeks or more after starting nevirapine) and asymptomatic increases in AST or ALT. Liver enzyme abnormalities (AST, ALT, GGT) were observed more frequently in subjects receiving nevirapine than in controls (see Table 3). Skin Reaction The most common clinical toxicity of nevirapine is rash, which can be severe or life-threatening [see Boxed Warning and Warnings and Precautions (5.2) ] . Rash occurs most frequently within the first 6 weeks of therapy. Rashes are usually mild to moderate, maculopapular erythematous cutaneous eruptions, with or without pruritus, located on the trunk, face and extremities. In controlled clinical trials (Trials 1037, 1038, 1046, and 1,090), Grade 1 and 2 rashes were reported in 13% of subjects receiving nevirapine compared to 6% receiving placebo during the first 6 weeks of therapy. Grade 3 and 4 rashes were reported in 2% of nevirapine recipients compared to less than 1% of subjects receiving placebo. Women tend to be at higher risk for development of nevirapine-associated rash [see Boxed Warning and Warnings and Precautions (5.2) ] . Treatment-related, adverse experiences of moderate or severe intensity observed in greater than 2% of subjects receiving nevirapine in placebo-controlled trials are shown in Table 2. Table 2 Percentage of Subjects with Moderate or Severe Drug-Related Events in Adult Placebo-Controlled Trials Trial 1090 1 Trials 1037, 1038, 1046 2 Nevirapine Placebo Nevirapine Placebo (n=1121) (n=1128) (n=253) (n=203) Median exposure (weeks) 58 52 28 28 Any adverse event 15% 11% 32% 13% Rash 5 2 7 2 Nausea 1 1 9 4 Granulocytopenia 2 3 250 U/L 5 4 14 4 SGOT (AST) >250 U/L 4 3 8 2 Bilirubin >2.5 mg/dL 2 2 2 2 Hematology Hemoglobin <8.0 g/dL 3 4 0 0 Platelets <50,000/mm 3 1 1 <1 2 Neutrophils <750/mm 3 13 14 4 1 1 Background therapy included 3TC for all subjects and combinations of NRTIs and PIs. Subjects had CD4 + cell counts less than 200 cells/mm 3 . 2 Background therapy included ZDV and ZDV+ddI; nevirapine monotherapy was administered in some subjects. Subjects had CD4 + cell count greater than or equal to 200 cells/mm 3 . Clinical Trial Experience in Pediatric Patients Adverse events were assessed in BI Trial 1100.1032 (ACTG 245), a double-blind, placebo-controlled trial of nevirapine (n=305) in which pediatric subjects received combination treatment with nevirapine. In this trial two subjects were reported to experience Stevens-Johnson syndrome or Stevens-Johnson/toxic epidermal necrolysis transition syndrome. Safety was also assessed in trial BI 1100.882 (ACTG 180), an open-label trial of nevirapine (n=37) in which subjects were followed for a mean duration of 33.9 months (range: 6.8 months to 5.3 years, including long-term follow-up in 29 of these subjects in trial BI 1100.892). The most frequently reported adverse events related to nevirapine in pediatric subjects were similar to those observed in adults, with the exception of granulocytopenia, which was more commonly observed in children receiving both zidovudine and nevirapine. Cases of allergic reaction, including one case of anaphylaxis, were also reported. The safety of nevirapine was also examined in BI Trial 1100.1368, an open-label, randomized clinical trial performed in South Africa in which 123 HIV-1 infected treatment-naïve subjects between 3 months and 16 years of age received combination treatment with nevirapine oral suspension, lamivudine and zidovudine for 48 weeks [see Use in Specific Populations (8.4) and Clinical Pharmacology (12.3)] . Rash (all causality) was reported in 21% of the subjects, 4 (3%) of whom discontinued drug due to rash. All 4 subjects experienced the rash early in the course of therapy (less than 4 weeks) and resolved upon nevirapine discontinuation. Other clinically important adverse events (all causality) include neutropenia (9%), anemia (7%), and hepatotoxicity (2%) [see Use in Specific Populations (8.4) and Clinical Studies (14.2) ] . Safety information on use of nevirapine in combination therapy in pediatric subjects 2 weeks to less than 3 months of age was assessed in 36 subjects from the BI 1100.1222 (PACTG 356) trial. No unexpected safety findings were observed although granulocytopenia was reported more frequently in this age group compared to the older pediatric age groups and adults. 6.2 Postmarketing Experience In addition to the adverse events identified during clinical trials, the following adverse reactions have been identified during post-approval use of nevirapine. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Body as a Whole: fever, somnolence, drug withdrawal [see Drug Interactions (7) ] , redistribution/accumulation of body fat [see Warnings and Precautions (5.6) ] Gastrointestinal: vomiting Liver and Biliary: jaundice, fulminant and cholestatic hepatitis, hepatic necrosis, hepatic failure Hematology: anemia, eosinophilia, neutropenia Investigations: decreased serum phosphorus Musculoskeletal: arthralgia, rhabdomyolysis associated with skin and/or liver reactions Neurologic: paraesthesia Skin and Appendages: Allergic reactions including anaphylaxis, angioedema, bullous eruptions, ulcerative stomatitis and urticaria have all been reported. In addition, hypersensitivity syndrome and hypersensitivity reactions with rash associated with constitutional findings such as fever, blistering, oral lesions, conjunctivitis, facial edema, muscle or joint aches, general malaise, fatigue, or significant hepatic abnormalities, drug reaction with eosinophilia and systemic symptoms (DRESS) [see Warnings and Precautions (5.1) ] plus one or more of the following: hepatitis, eosinophilia, granulocytopenia, lymphadenopathy, and/or renal dysfunction have been reported. In post-marketing surveillance anemia has been more commonly observed in children although development of anemia due to concomitant medication use cannot be ruled out.
Information for Patients
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Hepatotoxicity and Skin Reactions Inform patients of the possibility of severe liver disease or skin reactions associated with nevirapine that may result in death. Instruct patients developing signs or symptoms of liver disease or severe skin reactions to discontinue nevirapine and seek medical attention immediately, including performance of laboratory monitoring. Symptoms of liver disease include fatigue, malaise, anorexia, nausea, jaundice, acholic stools, liver tenderness or hepatomegaly. Symptoms of severe skin or hypersensitivity reactions include rash accompanied by fever, general malaise, fatigue, muscle or joint aches, blisters, oral lesions, conjunctivitis, facial edema, and/or hepatitis. Intensive clinical and laboratory monitoring, including liver enzymes, is essential during the first 18 weeks of therapy with nevirapine to detect potentially life-threatening hepatotoxicity and skin reactions. However, liver disease can occur after this period; therefore, monitoring should continue at frequent intervals throughout nevirapine treatment. Extra vigilance is warranted during the first 6 weeks of therapy, which is the period of greatest risk of hepatic events. Advise patients with signs and symptoms of hepatitis to discontinue nevirapine and seek medical evaluation immediately. If nevirapine is discontinued due to hepatotoxicity, do not restart it. Patients, particularly women, with increased CD4 + cell count at initiation of nevirapine therapy (greater than 250 cells/mm 3 in women and greater than 400 cells/mm 3 in men) are at substantially higher risk for development of symptomatic hepatic events, often associated with rash. Advise patients that co-infection with hepatitis B or C and/or increased transaminases at the start of therapy with nevirapine are associated with a greater risk of later symptomatic events (6 weeks or more after starting nevirapine) and asymptomatic increases in AST or ALT [see Warnings and Precautions (5.1) ] . The majority of rashes associated with nevirapine occur within the first 6 weeks of initiation of therapy. Instruct patients that if any rash occurs during the two-week lead-in period, do not escalate the nevirapine dose until the rash resolves. The total duration of the once-daily lead-in dosing period should not exceed 28 days, at which point an alternative regimen may need to be started. Any patient experiencing a rash should have their liver enzymes (AST, ALT) evaluated immediately. Patients with severe rash or hypersensitivity reactions should discontinue nevirapine immediately and consult a physician. Nevirapine should not be restarted following severe skin rash or hypersensitivity reaction. Women tend to be at higher risk for development of nevirapine -associated rash [see Warnings and Precautions (5.2) ] Administration and Missed Dosage Inform patients to take nevirapine every day as prescribed. Advise patients not to alter the dose without consulting their doctor. If a dose is missed, patients should take the next dose as soon as possible. However, if a dose is skipped, the patient should not double the next dose. To avoid overdose, inform patients that they should never take immediate-release nevirapine and extended-release nevirapine XR concomitantly. Drug Interactions Nevirapine may interact with some drugs; therefore, advise patients to report to their doctor the use of any other prescription, non-prescription medication or herbal products, particularly St. John's wort [see Warnings and Precautions (5.4) and Drug Interactions (7) ] . Immune Reconstitution Syndrome Advise patients to inform their healthcare provider immediately of any signs or symptoms of infection, as inflammation from previous infection may occur soon after combination antiretroviral therapy, including when nevirapine is started [see Warnings and Precautions (5.5) ] . Fat Redistribution Inform patients that redistribution or accumulation of body fat may occur in patients receiving antiretroviral therapy and that the cause and long-term health effects of these conditions are not known at this time [see Warnings and Precautions (5.6) ] . Pregnancy Registry Advise patients that there is a pregnancy registry that monitors pregnancy outcomes in women exposed to nevirapine during pregnancy [see Use in Specific Populations (8.1) ]. Lactation Instruct women with HIV-1 infection not to breastfeed because HIV-1 can be passed to the baby in the breast milk [see Use in Specific Populations (8.2) ]. Infertility Advise females of reproductive potential of the potential for impaired fertility from nevirapine [see Use in Specific Populations (8.3) and Nonclinical Toxicology (13.1) ] Manufactured for: Camber Pharmaceuticals, Inc. Piscataway, NJ 08854. By: HETERO TM Hetero Labs Limited Jeedimetla, Hyderabad - 500 055, India. Revised: 08/2022 logo
Clinical data sourced from openFDA drug labeling. For complete prescribing information, consult the full drug label.