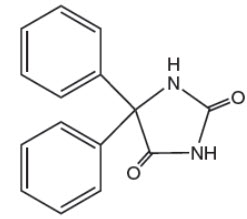
EXTENDED PHENYTOIN SODIUM CAPSULES, USP 100 MG 1000CT
Generic: Phenytoin Sodium
EXTENDED PHENYTOIN SODIUM CAPSULES, USP 100 MG 1000CT
Sign up to see pricing
Licensed pharmacies, clinics, doctor's offices, and veterinary practices get instant account approval
Sign Up — Instant ApprovalDrug Information
Identification
Phenytoin Sodium
Phenytoin Sodium
Sun Pharmaceutical Industries, Inc.
HUMAN PRESCRIPTION DRUG
Administration
CAPSULE, EXTENDED RELEASE
ORAL
ANDA040684
Active Ingredients
| Ingredient | Strength |
|---|---|
| PHENYTOIN SODIUM | 100 mg/1 |
Pharmacological Class
Data sourced from openFDA / DailyMed. For full prescribing information, consult the drug label.
Wholesale compliance resources
Drug Resources
Clinical Drug Information
Indications & Usage
1 INDICATIONS AND USAGE Extended phenytoin sodium capsules are indicated for the treatment of tonic-clonic (grand mal) and psychomotor (temporal lobe) seizures and prevention and treatment of seizures occurring during or following neurosurgery. Extended phenytoin sodium capsules are indicated for the treatment of tonic-clonic (grand mal) and psychomotor (temporal lobe) seizures and prevention and treatment of seizures occurring during or following neurosurgery. ( 1 )
Dosage & Administration
2 DOSAGE AND ADMINISTRATION Adult starting dose in patients who have received no previous treatment is one 100 mg extended phenytoin sodium capsule three times a day, with dose adjustments as necessary. For most adults, the satisfactory maintenance dose will be one capsule three to four times a day. An increase, up to two capsules three times a day may be made, if necessary. ( 2.1 ) Adult once-a-day dose: If seizure control is established with divided doses of three 100 mg extended phenytoin sodium capsules daily, once-a-day dosage with 300 mg extended phenytoin sodium capsules may be considered. ( 2.1 ) Adult loading dose: reserved for patients in a clinic or hospital setting who require rapid steady-state serum levels and where intravenous administration is not desired. Refer to full prescribing information. ( 2.1 ) Pediatric starting dose is 5 mg/kg/day in two to three equally divided doses, with dosage adjustments as necessary, up to a maximum of 300 mg daily. Maintenance dosage is 4 mg/kg/day to 8 mg/kg/day. ( 2.2 ) Serum blood level determinations may be necessary for optimal dosage adjustments—the clinically effective serum total concentration is 10 mcg/mL to 20 mcg/mL (unbound phenytoin concentration is 1 mcg/mL to 2 mcg/mL). ( 2.3 ) 2.1 Adult Dosage Divided daily dosage: The recommended starting dose for adult patients who have received no previous treatment is one 100-mg extended phenytoin sodium capsule by mouth three times daily. Adjust the dosage to suit individual requirements up to a maximum of two capsules three times a day. For most adults, the satisfactory maintenance dosage will be one capsule three to four times a day. Once-a-day dosage: In adults, if seizure control is established with divided doses of three 100-mg extended phenytoin sodium capsules daily, once-a-day dosage with 300 mg of extended phenytoin sodium capsules may be considered. Studies comparing divided doses of 300 mg with a single daily dose of this quantity indicated absorption, peak serum levels, biologic half-life, difference between peak and minimum values, and urinary recovery were equivalent. Once-a-day dosage offers a convenience to the individual patient or to nursing personnel for institutionalized patients and is intended to be used only for patients requiring this amount of drug daily. A major problem in motivating noncompliant patients may also be lessened when the patient can take this drug once a day. However, patients should be cautioned not to miss a dose, inadvertently. Only extended phenytoin sodium capsules are recommended for once-a-day dosing. Inherent differences in dissolution characteristics and resultant absorption rates of phenytoin due to different manufacturing procedures and/or dosage forms preclude such recommendation for other phenytoin products. When a change in the dosage form or brand is prescribed, careful monitoring of phenytoin serum levels should be carried out. Loading dose: Some authorities have advocated use of an oral loading dose of phenytoin in adults who require rapid steady-state serum levels and where intravenous administration is not desirable. This dosing regimen should be reserved for patients in a clinic or hospital setting where phenytoin serum levels can be closely monitored. Patients with a history of renal or liver disease should not receive the oral loading regimen. Initially, one gram of extended phenytoin sodium capsules is divided into three doses (400 mg, 300 mg, 300 mg) and administered at two-hour intervals. Normal maintenance dosage is then instituted 24 hours after the loading dose, with frequent serum level determinations. 2.2 Pediatric Dosage The recommended starting dosage for pediatric patients is 5 mg/kg/day by mouth in two or three equally divided doses, with subsequent dosage individualized to a maximum of 300 mg daily in divided doses. A recommended daily maintenance dosage is usually 4 mg/kg/day to 8 mg/kg/day in equally divided doses. Children over 6 years and adolescents may require the minimum adult dosage (300 mg/day). 2.3 Dosage Adjustments Dosage should be individualized to provide maximum benefit. In some cases, serum blood level determinations may be necessary for optimal dosage adjustments. Trough levels provide information about clinically effective serum level range and confirm patient compliance, and are obtained just prior to the patient's next scheduled dose. Peak levels indicate an individual's threshold for emergence of dose-related side effects and are obtained at the time of expected peak concentration. Therapeutic effect without clinical signs of toxicity occurs more often with serum total concentrations between 10 mcg/mL and 20 mcg/mL (unbound phenytoin concentrations between 1 mcg/mL and 2 mcg/mL), although some mild cases of tonic-clonic (grand mal) epilepsy may be controlled with lower serum levels of phenytoin. In patients with renal or hepatic disease, or in those with hypoalbuminemia, the monitoring of unbound phenytoin concentrations may be more relevant [see Dosage and Administration (2.5) ]. With recommended dosage, a period of seven to ten days may be required to achieve steady-state blood levels with phenytoin and changes in dosage (increase or decrease) should not be carried out at intervals shorter than seven to ten days. 2.4 Switching Between Phenytoin Formulations The free acid form of phenytoin is used in phenytoin oral suspension and phenytoin chewable tablets. Extended phenytoin sodium capsules and parenteral phenytoin are formulated with the sodium salt of phenytoin. Because there is approximately an 8% increase in drug content with the free acid form over that of the sodium salt, dosage adjustments and serum level monitoring may be necessary when switching from a product formulated with the free acid to a product formulated with the sodium salt and vice versa. 2.5 Dosing in Patients with Renal or Hepatic Impairment or Hypoalbuminemia Because the fraction of unbound phenytoin is increased in patients with renal or hepatic disease, or in those with hypoalbuminemia, the monitoring of phenytoin serum levels should be based on the unbound fraction in those patients [see Warnings and Precautions (5.11) and Use in Specific Populations (8.6) ] . 2.6 Geriatric Dosage Phenytoin clearance is decreased slightly in elderly patients and lower or less frequent dosing may be required [see Clinical Pharmacology (12.3) ] . 2.7 Dosing during Pregnancy Decreased serum concentrations of phenytoin may occur during pregnancy because of altered phenytoin pharmacokinetics. Periodic measurement of serum phenytoin concentrations should be performed during pregnancy, and the extended phenytoin sodium capsule dosage should be adjusted as necessary. Postpartum restoration of the original dosage will probably be indicated [see Use in Specific Populations (8.1) ]. Because of potential changes in protein binding during pregnancy, the monitoring of phenytoin serum levels should be based on the unbound fraction.
Adverse Reactions
6 ADVERSE REACTIONS The following serious adverse reactions are described elsewhere in the labeling: Withdrawal Precipitated Seizure, Status Epilepticus [see Warnings and Precautions (5.1) ] Suicidal Behavior and Ideation [see Warnings and Precautions (5.2) ] Serious Dermatologic Reactions [see Warnings and Precautions (5.3) ] Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity [see Warnings and Precautions (5.4) ] Hypersensitivity [see Warnings and Precautions (5.5) ] Cardiac Effects [see Warnings and Precautions (5.6) ] Angioedema [see Warnings and Precautions (5.7) ] Hepatic Injury [see Warnings and Precautions (5.8) ] Hematopoietic Complications [see Warnings and Precautions (5.9) ] Effects on Vitamin D and Bone [see Warnings and Precautions (5.10) ] Exacerbation of Porphyria [see Warnings and Precautions (5.12) ] Teratogenicity and Other Harm to the Newborn [see Warnings and Precautions (5.13) ] Hyperglycemia [see Warnings and Precautions (5.14) ] The following adverse reactions associated with the use of extended phenytoin sodium capsules were identified in clinical studies or postmarketing reports. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Body as a Whole: Allergic reactions in the form of rash and rarely more serious forms and DRESS have been observed, as has angioedema [see Warnings and Precautions (5.3 , 5.4 , 5.7) ] . Anaphylaxis has also been reported. There have also been reports of coarsening of facial features, systemic lupus erythematosus, periarteritis nodosa, and immunoglobulin abnormalities. Digestive System: Acute hepatic failure, toxic hepatitis, liver damage, nausea, vomiting, constipation, enlargement of the lips, and gingival hyperplasia. Hematologic and Lymphatic System: Hematopoietic complications, some fatal, have occasionally been reported in association with administration of phenytoin. These have included thrombocytopenia, leukopenia, granulocytopenia, agranulocytosis, and pancytopenia with or without bone marrow suppression. While macrocytosis and megaloblastic anemia have occurred, these conditions usually respond to folic acid therapy. Lymphadenopathy including benign lymph node hyperplasia, pseudolymphoma, lymphoma, and Hodgkin's disease have been reported [see Warnings and Precautions (5.9) ] . Pure red cell aplasia has also been reported. Laboratory Test Abnormality: Phenytoin may decrease serum concentrations of thyroid hormone (T4 and T3), sometimes with an accompanying increase in thyroid-stimulating hormone (TSH), but usually in the absence of clinical hypothyroidism. Phenytoin may also produce lower than normal values for dexamethasone or metyrapone tests. Phenytoin may cause increased serum levels of glucose [see Warnings and Precautions (5.14) ] , alkaline phosphatase, and gamma glutamyl transpeptidase (GGT). Nervous System: The most common adverse reactions encountered with phenytoin therapy are nervous system reactions and are usually dose-related. Reactions include nystagmus, ataxia, slurred speech, decreased coordination, somnolence, and mental confusion. Dizziness, vertigo, insomnia, transient nervousness, motor twitchings, paresthesias, and headaches have also been observed. There have also been rare reports of phenytoin-induced dyskinesias, including chorea, dystonia, tremor and asterixis, similar to those induced by phenothiazine and other neuroleptic drugs. Cerebellar atrophy has been reported, and appears more likely in settings of elevated phenytoin levels and/or long-term phenytoin use [see Warnings and Precautions (5.15) ] . A predominantly sensory peripheral polyneuropathy has been observed in patients receiving long-term phenytoin therapy. Skin and Appendages: Dermatological manifestations sometimes accompanied by fever have included scarlatiniform or morbilliform rashes. A morbilliform rash (measles-like) is the most common; other types of dermatitis are seen more rarely. Other more serious forms which may be fatal have included bullous, exfoliative or purpuric dermatitis, acute generalized exanthematous pustulosis, Stevens-Johnson syndrome, and toxic epidermal necrolysis [see Warnings and Precautions (5.3) ] . There have also been reports of hypertrichosis and urticaria. Special Senses: Altered taste sensation including metallic taste. Urogenital: Peyronie's disease The most common adverse reactions are nervous system reactions, including nystagmus, ataxia, slurred speech, decreased coordination, somnolence, and mental confusion. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Taro Pharmaceuticals U.S.A., Inc. at 1-866-923-4914 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
Information for Patients
17 PATIENT COUNSELING INFORMATION Advise patients to read the FDA-approved patient labeling (Medication Guide). Administration Information Advise patients taking phenytoin of the importance of adhering strictly to the prescribed dosage regimen, and of informing the physician of any clinical condition in which it is not possible to take the drug orally as prescribed, e.g., surgery, etc. Advise patients not to use capsules which are discolored. Withdrawal of Antiepileptic Drugs Advise patients not to discontinue use of extended phenytoin sodium capsules without consulting with their healthcare provider. Extended phenytoin sodium capsules should normally be gradually withdrawn to reduce the potential for increased seizure frequency and status epilepticus [see Warnings and Precautions (5.1) ] . Suicidal Ideation and Behavior Counsel patients, their caregivers, and families that AEDs, including extended phenytoin sodium capsules, may increase the risk of suicidal thoughts and behavior and advise them of the need to be alert for the emergence or worsening of symptoms of depression, any unusual changes in mood or behavior, or the emergence of suicidal thoughts, behavior, or thoughts about self-harm. Behaviors of concern should be reported immediately to healthcare providers [see Warnings and Precautions (5.2) ] . Serious Dermatologic Reactions Advise patients of the early signs and symptoms of severe cutaneous adverse reactions and to report any occurrence immediately to a physician [see Warnings and Precautions (5.3) ] . Potential Signs of Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) and Other Systemic Reactions Advise patients of the early toxic signs and symptoms of potential hematologic, dermatologic, hypersensitivity, or hepatic reactions. These symptoms may include, but are not limited to, fever, sore throat, rash, ulcers in the mouth, easy bruising, lymphadenopathy, facial swelling, and petechial or purpuric hemorrhage, and in the case of liver reactions, anorexia, nausea/vomiting, or jaundice. Advise the patient that, because these signs and symptoms may signal a serious reaction, that they must report any occurrence immediately to a physician. In addition, advise the patient that these signs and symptoms should be reported even if mild or when occurring after extended use [see Warnings and Precautions (5.3 , 5.4 , 5.5 , 5.8 , 5.9) ] . Cardiac Effects Counsel patients that cases of bradycardia and cardiac arrest have been reported, both at recommended phenytoin doses and levels, and in association with phenytoin toxicity. Patients should report cardiac signs or symptoms to their healthcare provider [see Warnings and Precautions (5.6) and Overdosage (10) ]. Angioedema Advise patients to discontinue extended phenytoin sodium capsules and seek immediate medical care if they develop signs or symptoms of angioedema, such as facial, perioral, or upper airway swelling [see Warnings and Precautions (5.7) ] . Effects of Alcohol Use and Other Drugs and Over-the-Counter Drug Interactions Caution patients against the use of other drugs or alcoholic beverages without first seeking their physician's advice [Drug Interactions (7.1, 7.2)] . Inform patients that certain over-the-counter medications (e.g., antacids, cimetidine, and omeprazole), vitamins (e.g., folic acid), and herbal supplements (e.g., St. John's wort) can alter their phenytoin levels. Hyperglycemia Advise patients that extended phenytoin sodium capsules may cause an increase in blood glucose levels [see Warnings and Precautions (5.14) ] . Gingival Hyperplasia Advise patients of the importance of good dental hygiene in order to minimize the development of gingival hyperplasia and its complications. Neurologic Effects Counsel patients that extended phenytoin sodium capsules may cause dizziness, gait disturbance, decreased coordination and somnolence. Advise patients taking extended phenytoin sodium capsules not to drive, operate complex machinery, or engage in other hazardous activities until they have become accustomed to any such effects associated with extended phenytoin sodium capsules. Use in Pregnancy Inform pregnant women and women of childbearing potential that use of extended phenytoin sodium capsules during pregnancy can cause fetal harm, including an increased risk for cleft lip and/or cleft palate (oral clefts), cardiac defects, dysmorphic skull and facial features, nail and digit hypoplasia, growth abnormalities (including microcephaly), and cognitive deficits. When appropriate, counsel pregnant women and women of childbearing potential about alternative therapeutic options. Advise women of childbearing potential who are not planning a pregnancy to use effective contraception while using extended phenytoin sodium capsules, keeping in mind that there is a potential for decreased hormonal contraceptive efficacy [see Drug Interactions (7.2) ]. Instruct patients to notify their physician if they become pregnant or intend to become pregnant during therapy, and to notify their physician if they are breastfeeding or intend to breastfeed during therapy [see Use in Specific Populations (8.1 , 8.2) ] . Encourage patients to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry if they become pregnant. This registry is collecting information about the safety of antiepileptic drugs during pregnancy [see Use in Specific Populations (8.1) ] .
Clinical data sourced from openFDA drug labeling. For complete prescribing information, consult the full drug label.